
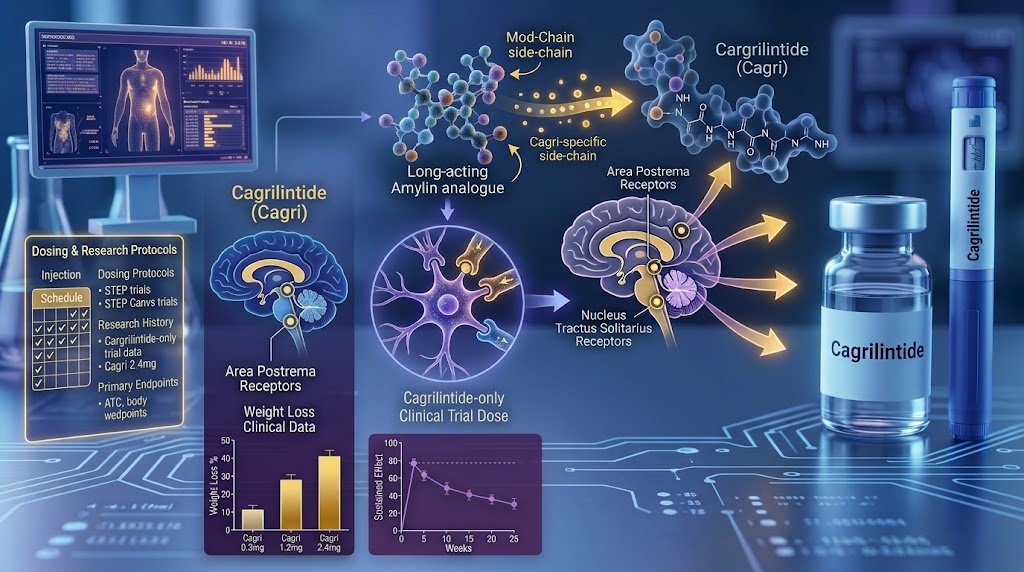
What Is Cagrilintide? Long-Acting Amylin Analogue Guide
Modern metabolic pharmacology has largely been shaped by incretin-based therapies that activate glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP) pathways. While these agents demonstrate marked efficacy in controlling blood glucose and reducing adiposity, clinical investigations increasingly highlight the limits of single-system receptor saturation. Escalating incretin doses often leads to gastrointestinal intolerance or metabolic plateaus, shifting investigative interest toward complementary, non-incretin pathways.
Cagrilintide represents the vanguard of this combinatorial approach. Developed by Novo Nordisk as a potent, long-acting amylin receptor analogue, cagrilintide introduces non-incretin neuroendocrine regulation to body weight management and glycemic control. Whether evaluated as a monotherapy or co-formulated alongside semaglutide in the dual therapy known as CagriSema, cagrilintide provides continuous amylin pathway activation on a convenient once-weekly cadence. This comprehensive guide breaks down cagrilintide’s chemical structure, receptor mechanisms, Phase 2/3 clinical trial evidence, established laboratory protocols, and synergistic research pairings.
Quick Summary: What Is Cagrilintide at a Glance?
Quick Answer: Cagrilintide is a synthetic, long-acting amylin analogue developed by Novo Nordisk. Featuring a C-terminal fatty diacid side chain for reversible albumin binding (~7 day half-life), it targets calcitonin/RAMP heterodimeric receptor complexes in the hindbrain. It delivers profound non-incretin satiety signaling, slowing gastric emptying and driving exceptional weight reduction when paired with Semaglutide as CagriSema.
| Protocol Parameter | Investigational Guidelines |
|---|---|
| Administration Route | Subcutaneous (Sub-Q) injection into adipose tissue |
| Administration Cadence | Once weekly (every 7 days), administered at any time of day |
| Initial Titration Phase | 0.16 mg to 0.3 mg once weekly for 4 weeks |
| Escalation Step 1 | 0.6 mg once weekly for 4 weeks |
| Escalation Step 2 | 1.2 mg once weekly for 4 weeks |
| Target Maintenance Dose | 2.4 mg once weekly (monotherapy or combined with 2.4 mg Semaglutide) |
| Key Monitored Biomarkers | Body weight, HbA1c, fasting glucose, fasting insulin, glucagon, lipid panel |
What Is Cagrilintide?
Cagrilintide is a synthetic, acylated peptide analogue of endogenous human amylin. Native amylin is a 37-amino-acid neuroendocrine hormone synthesized and co-secreted with insulin by pancreatic beta cells in response to nutrient intake. In healthy physiology, it coordinates postprandial glucose flux by slowing gastric transit, suppressing inappropriate post-meal glucagon secretion, and signaling satiety directly to the central nervous system.
Despite its physiological potency, wild-type human amylin cannot be effectively utilized in sustained laboratory protocols. It exhibits an elimination half-life of less than 15 minutes, undergoes rapid proteolytic degradation by neutral endopeptidases, and has a strong propensity to aggregate into insoluble, cytotoxic beta-sheet amyloid fibrils in solution. Cagrilintide addresses every structural limitation of native amylin:
- Lipidated Half-Life Extension: Cagrilintide incorporates a C-terminal fatty diacid side chain attached via a hydrophilic spacer. This lipid moiety enables high-affinity, reversible binding to circulating serum albumin, creating an endogenous depot that extends its elimination half-life to approximately 160 to 180 hours (~7 days).
- Aggregation Resistance: Strategic non-proteogenic amino acid substitutions along the core chain eliminate the fibrillogenic secondary structure, ensuring physical and chemical stability in liquid solution.
- Dual Satiety Signaling: Binds to calcitonin receptor (CTR) and receptor activity-modifying protein (RAMP) complexes, activating distinct meal-termination pathways in the hindbrain.
- Synergistic Co-Formulation: Formulated at a neutral pH that allows direct co-formulation with GLP-1 receptor agonists without chemical destabilization.
Mechanism of Action: Calcitonin & RAMP Receptor Complexes
Unlike single-protein incretin receptors, functional amylin receptors are heterodimeric complexes. They require the physical pairing of a core Calcitonin Receptor (CTR) with one of three accessory membrane proteins known as Receptor Activity-Modifying Proteins (RAMP1, RAMP2, or RAMP3):
- AMY1 Complex (CTR + RAMP1): Expressed throughout hindbrain nuclei; exhibits high affinity for both amylin and calcitonin gene-related peptide (CGRP).
- AMY2 Complex (CTR + RAMP2): Mediates balanced signaling across amylin and calcitonin receptor pathways.
- AMY3 Complex (CTR + RAMP3): Highly expressed in the area postrema and nucleus of the solitary tract (NTS); serves as a primary driver of central satiation.
When cagrilintide is administered, it engages these functional receptor heterodimers to trigger a coordinated cellular cascade:
- Heterodimer Docking: The acylated peptide docks into the transmembrane pocket formed by the CTR-RAMP interface, inducing a conformational realignment of transmembrane helix 6.
- Gαs Coupling & cAMP Generation: Active conformation recruits stimulatory G-protein alpha subunits, activating membrane-bound adenylyl cyclase to convert cytosolic ATP into cyclic adenosine monophosphate (cAMP).
- PKA & EPAC Signaling: Intracellular cAMP accumulation activates Protein Kinase A (PKA) and exchange proteins directly activated by cAMP (EPAC), initiating downstream phosphorylation cascades.
- Hindbrain Noradrenergic Firing: In the caudal dorsal vagal complex (area postrema and NTS), this signaling activates noradrenergic neurons projecting to the lateral parabrachial nucleus, generating robust meal-termination and fullness signals.
- Efferent Vagal Deceleration: Concurrently, efferent vagal signals decelerate gastric motility and suppress post-meal glucagon secretion from pancreatic alpha cells, stabilizing postprandial glucose entry without causing hypoglycemia.
Key Benefits of Cagrilintide in Metabolic Models
Preclinical evaluations and clinical trials confirm that cagrilintide delivers distinct metabolic advantages over traditional single-hormone regimens:
- True Multi-Pathway Synergy: Because amylin receptors and GLP-1 receptors occupy distinct anatomical circuits in the brain, cagrilintide acts synergistically with GLP-1 agonists. Combining the two mechanisms produces greater weight reduction and glycemic control than escalating either agent alone.
- Glucagon Regulation Without Hypoglycemia: Cagrilintide dampens inappropriate postprandial glucagon release from pancreatic alpha cells via paracrine signaling pathways rather than insulin-mediated suppression, smoothing out glycemic spikes safely.
- Delayed Gastric Emptying: Slows the delivery of chyme to the small intestine, blunting the rapid appearance of post-meal blood glucose while reinforcing mechanical satiety.
- Preservation of Skeletal Muscle: In obesity models, multi-pathway satiety enables substantial caloric restriction without the extreme gastrointestinal distress or severe muscle wasting frequently observed under aggressive single-agent GLP-1 starvation.
Clinical Trial Evidence: CagriSema Phase 2 & Phase 3 Highlights
While cagrilintide demonstrates significant independent efficacy as a monotherapy, its clinical prominence stems from trials evaluating its fixed-dose co-formulation with semaglutide (CagriSema):
1. Phase 2 Weight Loss in Overweight & Obesity
In a randomized, double-blind Phase 2 trial comparing cagrilintide monotherapy, semaglutide 2.4 mg monotherapy, and the CagriSema combination (cagrilintide 2.4 mg + semaglutide 2.4 mg) over 32 weeks:
- Superior Weight Reduction: Participants in the CagriSema combination arm achieved an average body weight loss of 15.6% at week 32, significantly exceeding cagrilintide monotherapy (8.1%) and semaglutide 2.4 mg monotherapy (5.1%) under identical trial conditions.
- Non-Plateaued Trajectory: Weight loss curves continued on a steady downward trajectory at 32 weeks, indicating extended therapeutic capacity across longer treatment durations.
2. Glycemic Control in Type 2 Diabetes
In a 32-week Phase 2 study evaluating individuals with type 2 diabetes inadequately controlled on metformin:
- HbA1c Reductions: CagriSema produced a mean HbA1c reduction of -2.2%, compared to -1.8% for semaglutide alone and -0.9% for cagrilintide alone.
- Glycemic Target Achievement: Over 89% of participants receiving CagriSema achieved an HbA1c of less than 7.0%, with a substantial cohort reaching normal fasting glucose levels (<5.7%).
3. Safety and Adverse Event Profile
The overall adverse event profile of cagrilintide is consistent with established metabolic peptide therapies:
- Gastrointestinal Symptoms: Mild-to-moderate, transient nausea, constipation, and vomiting were the most commonly reported side effects, typically manifesting during the initial dose-escalation phase and resolving as maintenance was reached.
- Discontinuation Rates: Treatment discontinuation rates due to adverse events remained low and comparable to standard GLP-1 monotherapy arms when appropriate 4-week titration intervals were utilized.
Documented Laboratory Research & Dosing Protocols
Published clinical trial architectures structure cagrilintide protocols around gradual dose titration to optimize gastrointestinal tolerability. Syringe units can be calculated using our free Peptide Calculator, while dosing schedules are organized inside the Protocol Tracker Tool.
Synergistic Research Pairings & Incretin Comparisons
Because cagrilintide acts via calcitonin/RAMP complexes rather than incretin pathways, research models frequently evaluate it alongside complementary metabolic and tissue-protective compounds:
- Semaglutide: The benchmark clinical pairing evaluated with cagrilintide. The combined formulation (CagriSema) engages both hypothalamic GLP-1 receptors and hindbrain amylin receptors, producing profound non-linear metabolic synergy. Review the underlying biology in our Semaglutide GLP-1 Research Guide and our detailed CagriSema Guide.
- Tirzepatide: Researchers benchmark cagrilintide’s non-incretin satiety mechanisms against the dual incretin (GIP/GLP-1) agonism of tirzepatide to compare single-receptor combination strategies with multi-incretin pathways. For a full breakdown, see our guide to Tirzepatide Dual Incretin Mechanisms.
- Retatrutide: In advanced metabolic studies examining triple GIP/GLP-1/Glucagon agonism, researchers reference amylin agonism to contrast receptor-mediated caloric expenditure with neuroendocrine meal-termination signaling. Review trial data in our Retatrutide Dosing & Trial Evidence Guide (or view Retatrutide research vials).
- Eloralintide: Compared side-by-side with alternative amylin analogues in our Eloralintide vs. Cagrilintide Comparison Guide and our Eloralintide Research Guide.
- Comprehensive Metabolic Landscape: Benchmark cagrilintide against the full spectrum of emerging agents in our Best GLP-1 for Weight Loss Guide.
- BPC-157: In preclinical investigations into gastrointestinal motility and mucosal barrier stability, research models evaluate whether co-administering cytoprotective pentadecapeptides supports mucosal adaptation during potent GLP-1/amylin titration. See our BPC-157 Mechanism & Research Protocols.
- TB-500: Teams analyzing cellular structural integrity, wound healing, and actin upregulation evaluate TB-500 (Thymosin Beta-4) alongside body composition protocols.
- GHK-Cu: For studies monitoring collagen synthesis, dermal remodeling, and extracellular matrix stability during significant adipose reduction, scientists reference the copper tripeptide detailed in our GHK-Cu Copper Tripeptide Guide.
Laboratory Handling, Reconstitution & Storage Standards
Maintaining the conformational integrity and chemical stability of long-acting amylin analogues requires strict adherence to laboratory cold-chain standards (detailed step-by-step in our Beginner's Guide to Peptides):
- Diluent Selection: Reconstitute lyophilized peptide vials using sterile, pharmaceutical-grade Pfizer Hospira Bacteriostatic Water containing 0.9% benzyl alcohol to prevent bacterial proliferation across multi-dose research protocols. For cell-culture or in-vitro binding assays sensitive to preservatives, utilize sterile 0.9% Sterile Bacteriostatic Saline.
- Reconstitution Technique: Direct the diluent stream smoothly down the inner glass wall of the vial using a sterile EasyTouch 31G Syringe. Do not spray diluent directly onto the lyophilized cake. Amylin analogues are sensitive to shear stress; gently roll or swirl the vial between your palms until completely dissolved. Avoid vigorous agitation or shaking. Review instructions on how to reconstitute peptides and how much bacteriostatic water to add.
- Storage Conditions: Store dry lyophilized powder at -20°C for long-term stability. Reconstituted liquid solutions must be kept refrigerated at 2°C to 8°C (36°F to 46°F), shielded from direct light and mechanical vibration within a dedicated Peptide Vial Case or insulated Compact Travel Case, and utilized within 28 to 30 days. Always verify third-party analytical documentation by learning how to read a peptide COA.
Cagrilintide demonstrates the therapeutic power of expanding beyond incretin mono-therapies into coordinated neuroendocrine receptor targeting. By delivering sustained, once-weekly activation of functional amylin and calcitonin receptor complexes, it represents a foundational cornerstone in the future of multi-pathway metabolic medicine.
← View all peptide guides, research & protocols in our Blog Archive





